

 The Science Behind Addyi: Clinical Trial Findings
How Flibanserin Alters Brain Chemistry to Increase Desire
Years of neuroscience research guided flibanserin’s development, revealing a subtle rewrite of motivational circuits. Rather than acting peripherally, it nudges central neurotransmitter balance, shifting how the brain evaluates sexual cues and desire-related salience.
At the receptor level it functions as a 5-HT1A agonist and 5-HT2A antagonist, outcomes that increase dopamine and norepinephrine in the prefrontal cortex. This biochemical tilt reduces inhibitory serotonin tone linked to low desire.
Those shifts modestly enhance reward signaling and attentional response to intimacy, translating into incremental gains in sexual motivation for some women. Effects appear over weeks, emphasizing population averages rather than dramatic individual transformations.
Clinically this explains modest but measurable changes, guiding expectations and management.
| Neurotransmitter | Change magnitude | Clinical relevance |
|---|---|---|
| Dopamine | Increase | Boosts reward signaling and sexual motivation |
| Serotonin | Decrease | Reduces inhibitory tone on desire circuits |
| Norepinephrine | Increase | Heightens arousal-related attention to sexual cues |
Landmark Clinical Trial Designs and Patient Selection Criteria
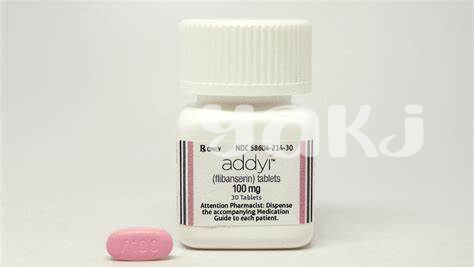
Early trials enrolled premenopausal women with distressing low desire and strict eligibility criteria, using randomized, placebo-controlled designs to isolate effects and measured hormonal and behavioral correlates.
Participants completed daily diaries and standardized scales, ensuring consistent symptom tracking while excluding psychiatric, relationship, or medical confounders and conducted sensitivity analyses for subgroup effects.
Dosing arms compared nightly addyi to placebo over months, with blinding preserved to limit expectation bias and capture real-time responses.
Careful selection improved signal detection but narrowed generalizability, a trade-off that shaped interpretation of efficacy for clinicians and regulators.
Primary Efficacy Outcomes and Meaningful Clinical Improvements
Clinical trials measured changes in sexual desire and frequency of satisfying sexual events using validated scales and daily diaries.
The medication produced small to modest mean improvements versus placebo, often translating into one to two additional satisfying sexual events per month. addyi showed consistent but variable effects across studies, with some patients reporting meaningful personal benefit.
Responder analyses helped identify those achieving clinically relevant gains, and secondary outcomes like sexual distress and relationship satisfaction provided broader context. Effect sizes were modest, prompting discussion about what constitutes meaningful improvement.
Clinicians weigh average trial results alongside individual goals, predicting who might benefit and monitoring response over time to guide shared treatment decisions. Expectations should be set realistically.
Safety Profile: Adverse Events and Risk Management Strategies
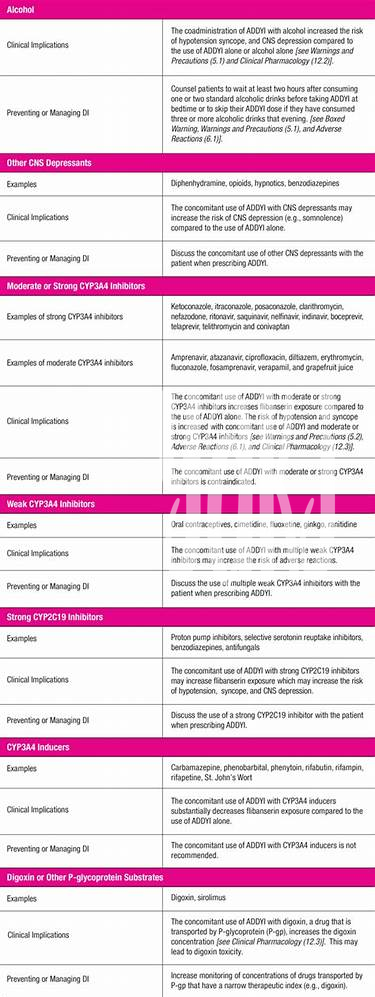
Participants often reported dizziness, nausea, and somnolence early in treatment. Rates varied by dose and patient characteristics in randomized trials.
Less common effects included hypotension and syncope, especially when alcohol or CYP3A4 inhibitors were involved. Careful selection excluded women with uncontrolled hypertension or heavy drinking histories.
Because of these risks, prescribers followed boxed warnings, contraindications, and strict counseling on avoiding alcohol and interacting medications. Education materials and periodic follow up reduced occurrences and supported informed consent.
Postmarketing surveillance and REMS-like communication reinforced monitoring strategies; for many patients addyi provided modest benefit when safety steps were observed. Longer term data continue to clarify rare safety signals and guide periodic updates to counseling, dosing, and follow-up intervals.
Controversies, Regulatory Debates, and Approval Journey
The path to approval for addyi unfolded like a medical thriller, mixing passionate advocacy with scientific scrutiny. Early trials produced modest benefits, sparking heated debate over clinical significance, trial designs, and whether endpoints reflected women’s lived experiences.
Regulators wrestled with safety signals—somnolence, hypotension with alcohol—and demanded risk mitigation strategies and labeling changes. Ultimately approval required additional data, postmarketing commitments, and a boxed warning, illustrating how science, policy, and public perception collide when treating female sexual desire disorders. Critics pushed for broader trials and patient-centered endpoints to better assess clinical value.
Real-world Effectiveness and Postmarketing Surveillance Findings
In clinical practice, many patients report modest but tangible improvements in sexual desire and relationship satisfaction after starting flibanserin, mirroring randomized trials. Real-world cohorts show small average gains, with a subset experiencing meaningful change. Adherence varies: discontinuation is common within months because benefits are slow to appear, side effects arise, or expectations are unmet.
Postmarketing surveillance has largely reaffirmed the trial safety profile while highlighting alcohol‑related hypotension and syncope risks when combined with interacting medications, prompting strict counseling and prescribing precautions. No widespread new safety crisis emerged, but clinicians emphasize careful patient selection, drug‑interaction checks, and ongoing assessment to identify responders and minimize harms in routine care and document outcomes over time to guide adjustments