

 Hydroxychloroquine Vs Chloroquine — Key Differences and Uses
Chemical Makeup and How Molecules Actually Differ
Two closely related antimalarial molecules trace their roots to quinoline rings, but a small functional tweak changes their behavior. One bears an extra hydroxyl group on the side chain, altering polarity and metabolic fate significantly.
This hydroxyl addition increases water solubility and influences distribution, while the parent compound remains more lipophilic. Such a modest structural difference affects how cells take up the drugs and how long they persist in tissues.
Metabolic pathways diverge too: liver enzymes process the molecules differently, producing distinct metabolites that can alter activity and toxicity. These subtle chemical shifts help explain varied dosing recommendations and risk profiles seen in clinical practice.
Understanding the atomic change turns abstract chemistry into clinical effects: solubility, tissue affinity, metabolism and side‑effect likelihood. Clinicians and patients benefit from recognizing how one small group transforms a familiar scaffold with important therapeutic consequences.
| Feature | Hydroxychloroquine | Chloroquine |
|---|---|---|
| Side chain | Contains hydroxyl group — more polar | Hydrogen in place — more lipophilic |
How They Work Mechanisms Explained for Patients
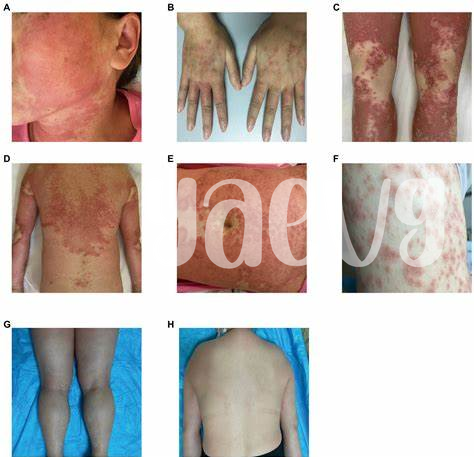
Imagine tiny sponges inside cells that soak up acid and slow certain processes. By accumulating in acidic compartments, drugs raise pH and can hinder how some viruses enter cells and how immune cells process antigens. Hydroxychloroquine works this way, altering cellular trafficking and reducing pathogen replication in lab models.
They also dampen toll-like receptor signaling, lower cytokine and interferon release, and calm overactive immune responses in lupus and rheumatoid arthritis. Effects are gradual and dose-dependent, reflecting combined chemical, cellular and immune actions that explain varied clinical responses in many patients.
Approved Medical Uses and Off Label Applications
In clinics, familiar stories begin with autoimmune diagnoses: lupus and rheumatoid arthritis patients often find symptom relief when treated with hydroxychloroquine and related agents.
Hydroxychloroquine is approved for malaria treatment and long-term management of certain autoimmune conditions; chloroquine shares malaria indications but differs in dosing and tolerability.
Beyond approvals, both drugs have seen off-label use for dermatologic disorders, chronic Q fever, and as adjuncts in some rheumatologic regimens, though supporting evidence varies.
Clinicians balance potential benefits against risks, relying on guidelines, monitoring, and evolving research to decide when off-label prescribing is appropriate. Shared decision-making with patients, informed consent, and periodic cardiac and ophthalmologic screening are commonly recommended when considering extended off-label therapy in real-world practice.
Safety Profiles Side Effects and Cardiac Concerns
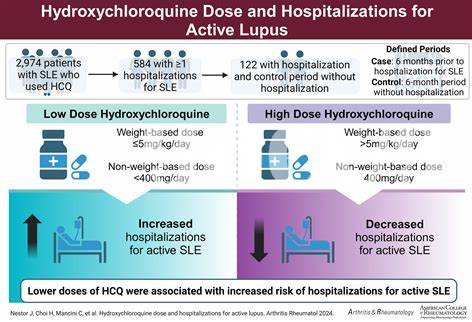
Clinicians note hydroxychloroquine is usually better tolerated than chloroquine; common reactions include nausea, diarrhea, rash and headache, while cumulative retinal toxicity emerges after prolonged therapy requiring regular ophthalmic monitoring often.
Cardiac risks can be serious: both drugs may prolong the QT interval, increasing torsades risk when combined with other QT-prolonging medications or in patients with hypokalemia, bradycardia, or heart disease.
Prescribers adjust dosing for renal or hepatic impairment and older adults; monitor ECG, electrolytes and vision, avoid interacting drugs like digoxin or antacids, and advise patients to report palpitations promptly.
Dosing Guidelines Interactions and Special Population Cautions
Clinicians tailor hydroxychloroquine doses to indication and body weight, making individualized plans. Children, pregnant patients and people with renal impairment require calculated reductions and close monitoring to prevent accumulation and toxicity while preserving therapeutic benefit.
Drug interactions matter: combining QT prolonging agents or some antivirals amplifies cardiac risk, so medication review and ECG monitoring are recommended. Hepatic impairment, concomitant immunomodulators and electrolyte disturbances influence dose choices and surveillance.
| Group | Action |
|---|---|
| Pregnancy | Consult |
| Renal | Reduce dose |
Older adults need lower starting doses and frequent vision checks for retinopathy; pregnancy decisions weigh maternal benefit versus fetal uncertainty. Shared decision making, baseline labs and clear follow up plans reduce harm and support safe, personalized therapy and cardiac monitoring
Evidence Landscape Controversies Pandemic Lessons and Practical Takeaways
Early laboratory signals and small clinical reports sparked intense interest in hydroxychloroquine and chloroquine during the COVID-19 crisis, but larger randomized trials failed to confirm benefit. Conflicting observational studies, politicization, and variable dosing compounded confusion. Clinicians learned the value of rigorous trial design and the danger of extrapolating in vitro activity to clinical efficacy. Clearer communication about uncertainty and rapid, well-powered studies proved critical to protect patients and guide practice.
Practical takeaways emphasize evidence-led prescribing: reserve these agents for approved autoimmune or malaria indications, avoid off-label use without trial oversight, and assess QT risk, electrolyte status, and drug interactions before prescribing. When considered experimentally, use standardized dosing, informed consent, and active safety monitoring. For patients, clear counseling about limited benefit for viral infections, potential cardiac risks, and the importance of following public health recommendations remains essential and contacting clinicians early.